

The Real Cost of Long-Term Care in Florida — And Why It Matters Sooner Than You Think
Trever Dahms • 8 June 2026
Most people in their 50s and 60s have a vague sense that long-term care is "expensive." Few have actually seen the numbers. When you do, the conversation about whether to plan for it changes pretty quickly..
The body content of your post goes here. To edit this text, click on it and delete this default text and start typing your own or paste your own from a different source.

If you've ever sat through a presentation about long-term care, you've probably heard this one: about 70% of people turning 65 will need long-term care at some point. I've used that number myself. It's true, and it matters. But a recent article on InsuranceNewsNet, What 70% doesn't tell you , made me rethink how I talk about it. The author, Chuck Greenblott, has run nursing homes and advised families on their finances, and his point is simple: a statistic isn't a plan. I think it's worth a few minutes of your time, so here's my quick summary and what it means for families here in the Tampa Bay area. The quick summary Where the 70% comes from: A 2019 study from the U.S. Department of Health and Human Services found that 70% of adults who reach age 65 will develop severe long-term care needs before they pass. "Severe" meant needing help with at least two everyday activities, like bathing or dressing, for 90 days or more, or having serious memory or cognitive problems. The number hiding in plain sight: In that same study, only 48% received any paid care. The difference between 70% and 48% is people who needed serious help and got it only from unpaid caregivers, usually family. The big idea: The 70% figure tells you how likely you are to need help. It doesn't tell you who will provide it, how long it will last, what it will cost, or what you or your family might have to give up. Greenblott suggests starting with real questions about your life instead of leading with a number. My take: three things worth thinking about 1. Unpaid care is not free care When a spouse or adult child steps in to help, nobody sends a bill. But that help often comes with a real price: cutting back hours at work, lost income, smaller retirement savings, and a toll on the caregiver's own health. I see this all the time. A plan that quietly assumes "my wife will take care of me" or "my daughter lives nearby" is still a plan, but it should be a conscious one that you've actually talked through with them. 2. Not everyone has a built-in caregiver Many people don't have a spouse at home or an adult child down the street. That's especially true here in Florida, where so many retirees moved away from family to enjoy the sunshine. If you live alone, the most urgent question isn't "Will I need care?" It's "Who will actually be there, and who do I trust to make decisions if I can't?" 3. The real goal is keeping your choices Good planning isn't about buying a policy because a scary number came up on a slide. It's about protecting the things that matter to you: staying in your own home as long as possible, choosing who cares for you, protecting your spouse's lifestyle, and not having your savings drained in a crisis. A little more context: what care costs and what Medicare covers What care costs in Florida. According to the 2024 Genworth and CareScout Cost of Care Survey, the median annual cost in Florida was about $68,640 for a home health aide and about $63,885 for assisted living. Nationally, the 2025 survey puts the median for assisted living at $6,200 a month, or $74,400 a year, up 5% from the year before. Nursing home care runs higher: Caring.com estimates a semi-private room in Tampa at roughly $9,900 a month. Costs vary by provider and keep rising, so treat these as ballpark figures. What Medicare does and doesn't cover. This surprises a lot of people. Medicare does not pay for long-term custodial care, which is help with daily activities like bathing, dressing, and eating. It can cover a short stay in a skilled nursing facility after a qualifying hospital stay of at least three days, but only while you need skilled care, and for no more than 100 days, with a daily copay after day 20. Medicaid can pay for long-term care, but it has strict income and asset limits, which often means spending down savings first. In other words, for most families the bill lands on their own savings or on their family's time unless they plan ahead. Ways people plan for it There's no one-size-fits-all answer, and that's exactly why the conversation matters. Common options include: Traditional long-term care insurance: dedicated coverage for care at home, in assisted living, or in a nursing home. Hybrid life and long-term care policies: life insurance that lets you use the benefit for care if you need it. If you never need care, your beneficiaries receive the death benefit. Life insurance with chronic illness riders: some policies, including many indexed universal life (IUL) policies, let you access part of the death benefit early if you can't perform daily activities. Annuities with long-term care features: certain annuities can increase your income or provide extra benefits if you need care. A self-funding plan: setting aside specific assets and knowing exactly how you'd use them. The legal pieces: a durable power of attorney and a designated health care surrogate, ideally set up with an estate planning attorney, so the people you trust can act for you. Questions worth asking yourself Before you think about any product, sit with these: If I needed help tomorrow, who would realistically be there? What would helping me cost them in time, money, and health? Where would I want to receive care: at home, in assisted living, or somewhere else? What am I most afraid of losing? Who would make decisions for me if I couldn't, and do they know my wishes? Let's talk it through If these questions stirred something up, that's a good thing. My approach is education first and no pressure. We start with your situation and your goals, and only then look at whether any coverage makes sense. As an independent broker, I work with 70+ carriers, so I can compare options rather than push a single company's product. If you're in Pinellas, Hillsborough, or Pasco County and want to talk through your long-term care plan, give me a call at (727) 314-3114 or visit tdcoverage.com .

AEP Isn't Just a Formality. It's Your One Guaranteed Shot All Year. Every year between October 15 and December 7, millions of people on Medicare get the chance to make changes to their coverage. Most people know the dates. Fewer people know how much can go wrong if they rush through it, or worse, ignore it completely. I've sat across the table from a lot of clients who came to me after AEP had already closed, wishing they'd made a different decision, or any decision at all. Here are the five mistakes I see most often, and how to steer clear of them this year. Mistake #1: Assuming Your Plan Is Staying the Same This is the big one. Every fall, insurance companies update their plans for the following year, and those changes can be significant. Premiums shift. Copays change. Drug formularies get revised, sometimes moving a medication you take regularly to a higher cost tier, or dropping it from coverage altogether. Provider networks can narrow too, meaning a doctor you've seen for years might no longer be in-network. Your plan mails you an Annual Notice of Change (ANOC) every September for exactly this reason, and it's one of the most skipped pieces of mail a Medicare beneficiary receives. If you didn't read yours, or can't find it, that's the first thing to track down before AEP ends. Mistake #2: Picking a Plan Based on Premium Alone A $0 premium plan can look like a win on paper, but premium is only one piece of the real cost. What matters more over the course of a year is your total out-of-pocket exposure: copays for specialist visits, the cost of your specific medications under that plan's formulary, and whether your preferred providers and hospitals are in-network. I've seen clients save $40 a month switching to a lower-premium plan, only to lose far more than that in higher specialist copays or a medication that jumped from Tier 2 to Tier 4. The plan that costs the least upfront isn't always the plan that costs the least overall. Mistake #3: Not Double-Checking the Pharmacy and Drug List Formularies change every year, and so do preferred pharmacy networks. A pharmacy that was your plan's preferred option last year might not be this year, which can mean paying noticeably more for the exact same prescription at the exact same counter. Before AEP ends, it's worth confirming two things: that every medication you take is still covered at a tier you're comfortable with, and that your pharmacy is still in the plan's preferred network. Both can change quietly, and neither shows up unless you go looking. Mistake #4: Waiting Until the Last Week AEP runs for seven weeks, but a lot of people treat it like a seven-day window because they put it off. The problem is that plan comparisons take time to do right, especially if you're managing multiple medications or specific provider relationships. Rushed decisions in the final days of AEP are where most of the regret comes from. Starting early gives you room to actually compare options, ask questions, and make a decision you're confident in, rather than a decision made under pressure because the deadline is two days away. Mistake #5: Going It Alone When You Don't Have To Medicare plans aren't standardized the way Medigap plans are. Two Advantage plans with similar-sounding names can have very different networks, drug coverage, and extra benefits. Comparing them accurately takes more than a quick glance at a brochure. This is really the whole reason agents like me exist. There's no cost to you for working with a licensed, independent agent, and you get someone who can compare plans across carriers instead of just one company's offerings. That's a different experience than calling a single carrier's 1-800 number, where the person on the other end can only talk about their own plans. The Bottom Line AEP closes on December 7, and whatever you decide, or don't decide, locks in for the full following year. If you haven't reviewed your coverage yet, now is the time, not the first week of December. If you want a second set of eyes on your current plan, or just want to know whether it's still the right fit for 2027, reach out and let's go through it together. No pressure, no cost, just a straight answer.

The Question Every Family Asks Eventually When a parent or spouse is diagnosed with dementia or Alzheimer's, one of the first questions families ask is what Medicare will cover. It's an important question, and unfortunately the answer is often not what families hope to hear. Original Medicare does not cover round-the-clock supervision or custodial care. That includes help with bathing, dressing, eating, or keeping someone safe if they wander. This is true even when the underlying diagnosis is dementia or Alzheimer's. What Medicare Will Cover Medicare can help with skilled home health care, but only under specific conditions: The patient must be considered homebound A doctor must certify the need for care and create a plan of care The care must involve skilled services, such as nursing visits, physical therapy, or speech therapy A home health aide can be included, but only as part of a skilled care plan, and hours are limited Medicare can also cover a limited stay in a skilled nursing facility after a qualifying hospital stay, but this is meant for short-term rehabilitation, not long-term custodial care. Where Medicaid Fits In Medicaid can cover long-term custodial care, including nursing home care and in some states in-home care, but only after a person has spent down most of their assets to meet the program's financial limits. For a lot of families, this means selling a home, spending savings, and going through a process that feels invasive at a time that's already emotionally difficult. It's not a bad option, it's just a last resort option, and it works best when families understand it ahead of time rather than in the middle of a crisis. Why I Bring Up Long Term Care Insurance Early This is exactly why I talk to clients about Long Term Care Insurance before they need it, especially if there's a family history of dementia or Alzheimer's. LTC insurance, or hybrid life and LTC policies, are really the only tools that let people plan ahead for this kind of care instead of reacting to it during a crisis. If you have a parent recently diagnosed, or you're thinking ahead for yourself, let's talk through what coverage actually looks like for your situation. Understanding your options now gives you and your family a lot more control later.
Term life insurance tends to get pitched as a young person's product — something you buy in your 30s to protect a growing family, and then quietly let expire once the kids are grown. That's a fair use case, but it's not the whole story. For some people, term life still has a role to play well into their 50s, 60s, and beyond.

LTC Policies Aren't One Size Fits All. Long Term Care Insurance is one of those products where two policies can look similar on the surface and be completely different once you dig into the details. If you're comparing quotes, here are the features I always walk clients through.

I think about all the people out there running the exact same Medicare Advantage plan they picked six or seven years ago, never once checking if it's still any good, kind of like people who still use the ringtone their phone came with because changing it never occurred to them. It was fine once. That doesn't mean it's still fine now. The Annual Enrollment Period (October 15 through December 7) is your one shot a year to actually do something about it. Here are five signs worth paying attention to.
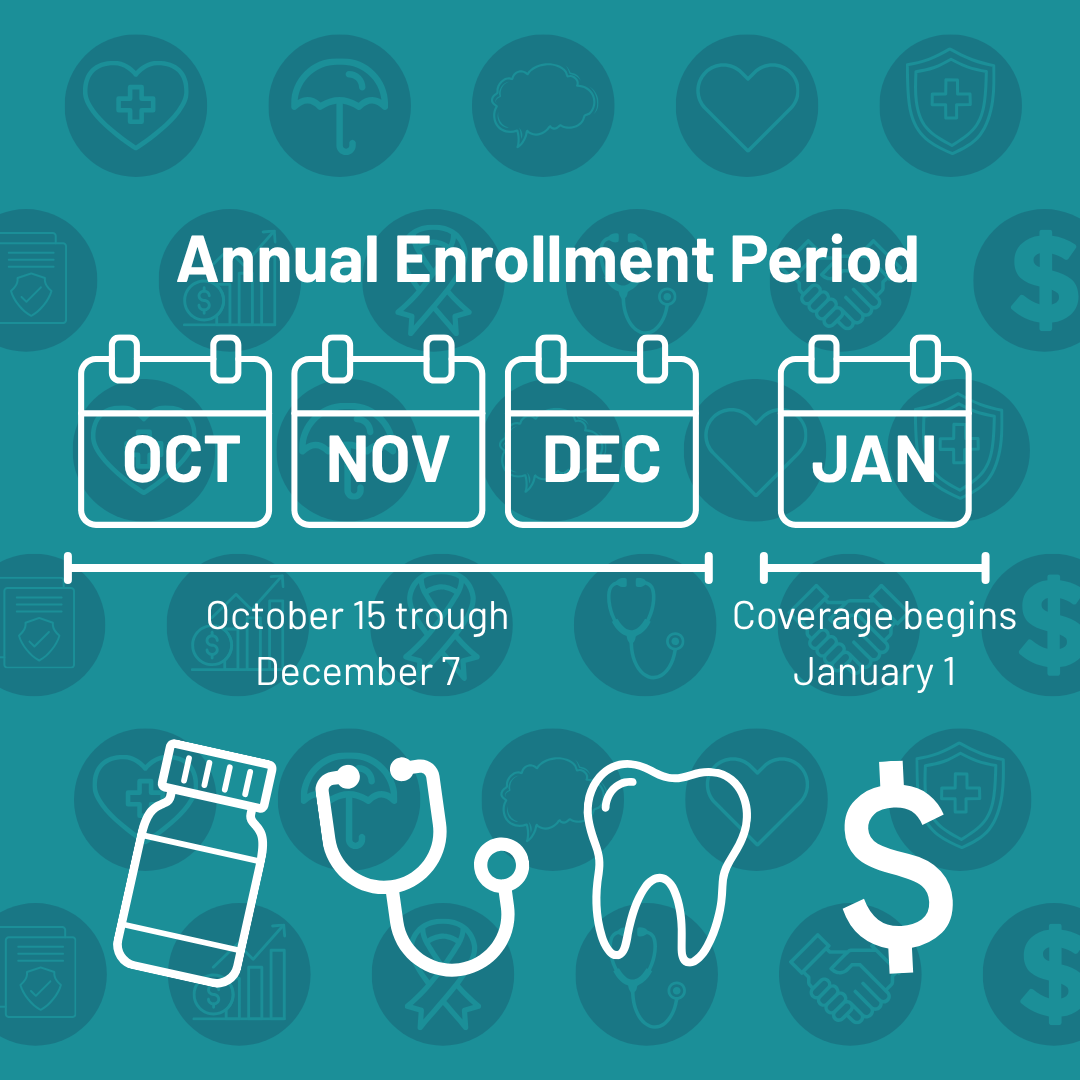
Okay so every October the same thing happens. Your mailbox turns into a warzone of postcards, all claiming to be the best plan, none of them actually explaining the rules of the game you're supposedly playing. It's like getting twelve different group texts about a party and nobody mentions the address. You're just standing there thinking, "Do I need to actually DO something here, or is this just insurance companies being insurance companies?

Medicare Covers a Lot. It Doesn't Cover Everything.

A Small Policy That Solves a Big Problem

Two Different Tools for Two Different Goals Clients often come to me asking about annuities without knowing there are different types built for different purposes. Two of the most common are Multi-Year Guaranteed Annuities, or MYGAs, and Fixed Index Annuities, or FIAs. They're both about protecting principal, but they work differently.